Kyphoplasty for Compression Fractures | Amit Sharma, MD
This animation demonstrates the OmniCurve® curved-balloon kyphoplasty workflow used by Dr. Sharma. The exact approach may vary according to the fracture pattern and the patient’s anatomy. Video used with permission from Stryker.
Written by Amit Sharma, MD
Interventional spine and pain physician, founder of SpinePain Solutions, and fellowship-trained at Johns Hopkins. Dr. Sharma has performed kyphoplasty and vertebral augmentation procedures for 22 years.
Kyphoplasty is a minimally invasive vertebral augmentation procedure used to stabilize selected painful vertebral compression fractures. A balloon is placed inside the fractured vertebral body, inflated to create a cavity and sometimes reduce part of the collapse, and then removed. Polymethylmethacrylate, or PMMA, bone cement is placed into the treated area to stabilize the broken bone.
Kyphoplasty may be considered for fractures caused by osteoporosis, selected traumatic injuries, or cancer involving a vertebra. Those groups are not interchangeable. Each requires a different evaluation of fracture activity, mechanical stability, posterior-wall integrity, neural compression and the need for additional treatment.
Quick Answer
- Osteoporosis: The most common clinical setting; kyphoplasty may fit an active painful fracture that limits mobility and has not improved adequately with appropriate nonsurgical care.
- Trauma: May fit selected stable compression or carefully evaluated incomplete burst patterns, but not an unstable injury or fracture causing important neural compression.
- Cancer or myeloma: May stabilize a painful pathological fracture, but it does not treat the tumor and must be coordinated with the oncologic plan.
- Across all causes: The fracture must be clinically relevant and anatomically suitable for controlled cement augmentation.
What Is Kyphoplasty and What Does It Treat?
A vertebral compression fracture occurs when a spinal bone partially collapses. The fracture can cause focal mid-back or lower-back pain that worsens with standing, walking, coughing, rolling in bed or changing position. Severe pain can reduce walking, sleep and independence, particularly in older adults.
Kyphoplasty treats the fractured vertebral body. It does not directly decompress the spinal canal, fuse adjacent vertebrae or correct every fixed deformity. Its principal objective is to stabilize painful fracture motion from within the vertebra. Partial restoration of vertebral height may occur when the fracture remains mobile, but height restoration is variable and is not the sole measure of success.
An imaging abnormality alone is not enough. Many patients have old compression deformities that are no longer painful. History, focal examination findings and imaging must identify the same active fracture.
A compressed vertebra is not automatically an indication for kyphoplasty.
The important question is whether the fracture remains active and is responsible for the current pain and loss of function. MRI is often helpful because marrow edema can support that determination.
Is Kyphoplasty Appropriate for Osteoporotic, Traumatic and Cancer-Related Fractures?
Kyphoplasty may have a role in all three categories, but candidacy differs substantially. Cause, morphology and stability must be assessed together.
| Fracture Cause | When Kyphoplasty May Fit | When Another or Additional Pathway Is Needed |
|---|---|---|
| Osteoporosis | Active painful compression fracture corresponding with the examination and imaging; persistent pain or mobility loss despite appropriate nonsurgical care | Healed or asymptomatic deformity, rapidly improving symptoms, pain from another structure, major instability or neural compression |
| Trauma | Selected stable compression fractures or carefully assessed Type A patterns without an urgent neurological or instability indication | Posterior-ligament injury, translation, progressive deformity, substantial retropulsion, unstable burst fracture or neurological deficit |
| Cancer or myeloma | Painful pathological compression fracture with a mechanical pain component that can be safely stabilized with cement | Epidural tumor, spinal-cord compression, extensive cortical destruction, infection or instability requiring decompression, fixation or reconstruction; oncologic treatment remains necessary |
Osteoporotic Compression Fractures
This is the most established everyday application. A typical candidate has new focal pain, reduced mobility and an acute or subacute fracture that remains active on MRI. A minor fall, lifting event or even ordinary movement may trigger a fracture when the bone is severely weakened.
Kyphoplasty is not required for every osteoporotic fracture. Analgesic treatment, bracing when appropriate and gradual mobilization may be reasonable when pain is manageable and function is improving. Procedural consideration becomes more relevant when pain remains severe, mobility is deteriorating or conservative treatment is not providing adequate progress.
Traumatic Compression and Burst Fractures
The word traumatic covers a wide range of injuries. A stable wedge compression fracture is very different from a fracture with posterior-ligament disruption, vertebral translation or bone pushed into the spinal canal. Kyphoplasty may be used alone in selected stable patterns or combined with posterior instrumentation in selected cases, but it cannot substitute for fixation when the spine is mechanically unstable.
CT is often important for defining cortical disruption and canal involvement. MRI can assess neural structures, ligaments and fracture activity. Progressive deformity, significant retropulsion or neurological loss requires spine-trauma evaluation rather than cement augmentation alone.
Cancer-Related and Myeloma Fractures
Metastatic disease and multiple myeloma can weaken a vertebra and create painful mechanical instability. Kyphoplasty may reduce fracture-related pain and improve function in selected patients, but it does not remove or cure the cancer.
Evaluation should address:
- Whether the pain is mechanical, tumor-related, neurological or mixed
- Whether epidural disease or spinal-cord compression is present
- The degree of posterior-wall and cortical destruction
- Whether tissue diagnosis or biopsy is needed
- Whether tumor ablation should accompany augmentation
- The roles and timing of radiation, systemic therapy or surgery
- Whether the vertebra requires fixation beyond cement augmentation
The CAFE randomized trial found faster functional improvement with balloon kyphoplasty than nonsurgical management in a selected group of patients with cancer-related vertebral compression fractures. Those results should not be generalized to patients with spinal-cord compression, extensive epidural tumor or gross instability.
Who May Be a Candidate for Kyphoplasty?
The strongest candidate generally has a painful active fracture that limits essential function and can be treated safely through vertebral augmentation.
| Findings Supporting Consideration | Findings Requiring Another Pathway or More Evaluation |
|---|---|
| Focal pain corresponding with a recent vertebral compression fracture | Incidental old compression deformity without matching symptoms |
| MRI marrow edema or another accepted sign of an active fracture | Pain primarily from a disc, facet joint, muscle, sacroiliac joint or another vertebra |
| Pain limiting walking, standing, sleep, breathing mechanics or daily care | Progressive weakness, spinal-cord compression or another neurological emergency |
| Inadequate improvement with an appropriate individualized trial of conservative care | Symptoms already improving sufficiently with nonsurgical treatment |
| Anatomy permitting controlled access and cement placement | Major posterior-wall destruction, severe canal compromise or mechanical instability |
| Acceptable infection, bleeding, anesthesia and cardiopulmonary risk | Active infection, uncorrected coagulopathy or uncontrolled medical illness |
Why MRI Often Matters
An X-ray can show vertebral height loss but may not establish when the fracture occurred. MRI can identify marrow edema, evaluate neural structures and help distinguish an active fracture from an old healed deformity. CT may be more useful for detailed cortical anatomy, posterior-wall disruption and traumatic fracture morphology. Imaging selection depends on the clinical situation.
When Kyphoplasty Is Not Enough
Kyphoplasty does not directly remove retropulsed bone or epidural tumor from the spinal canal. It also does not provide the same stability as instrumented spinal fixation. Neurological compression, major instability, severe deformity, infection or another pain generator may require a different or combined treatment plan.
How Kyphoplasty Is Performed
Kyphoplasty is performed under fluoroscopic imaging. The anesthesia, access route and number of treated vertebrae depend on the patient’s medical condition, fracture anatomy and clinical setting.
Preparation, Positioning and Imaging
Symptoms, examination and imaging are reviewed before treatment. Medications, allergies, infection risk, coagulation status and cardiopulmonary conditions are assessed. The patient is generally positioned face down and receives local anesthesia with monitored sedation or general anesthesia according to the individualized plan. Fluoroscopy is used to confirm the vertebral level and guide each instrument.
The OmniCurve Curved-Balloon Workflow
The sequence below demonstrates the OmniCurve® curved-balloon system and the unipedicular workflow Dr. Sharma uses in appropriate cases. Other kyphoplasty systems and access routes may use different instruments or somewhat different steps.
1. Insert the Curved Introducer
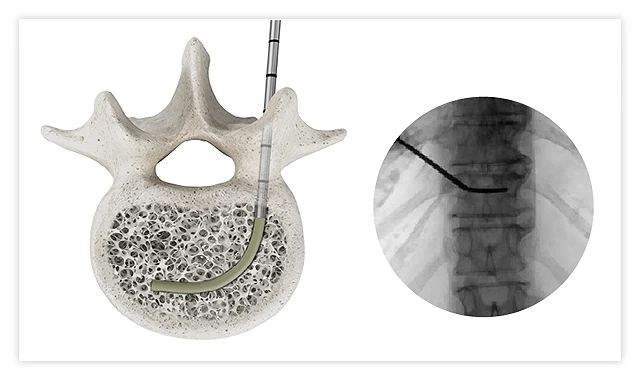
The introducer and radiopaque sheath are advanced through the pedicle and directed across the vertebral body under fluoroscopic guidance.
2. Leave the Sheath in Position
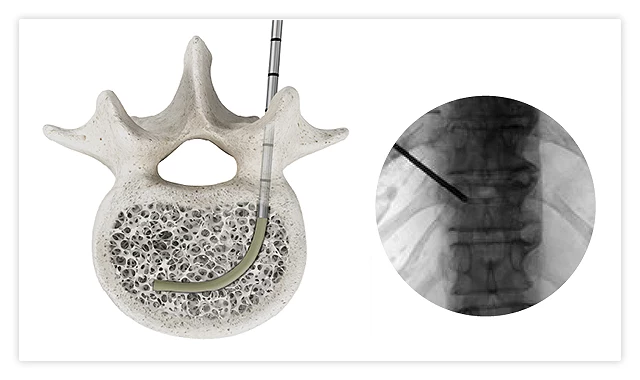
The introducer is removed while the curved sheath remains in the planned position inside the fractured vertebra.
3. Position the Balloon
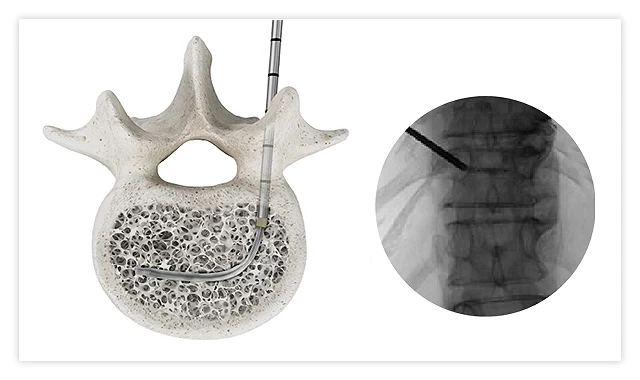
The balloon catheter is advanced through the sheath to the intended treatment area.
4. Expose the Balloon
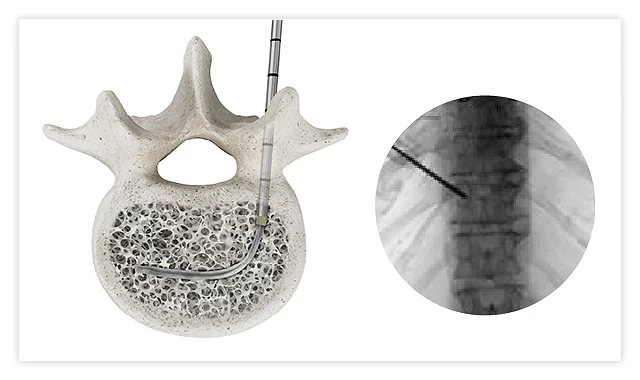
The sheath is retracted to expose the balloon within the vertebral body.
5. Inflate the Balloon
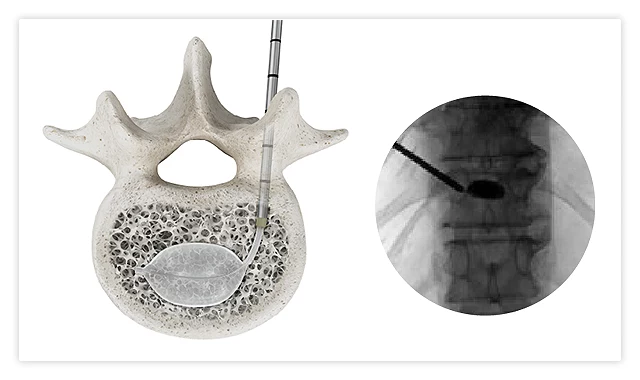
The balloon is inflated under imaging guidance to create a cavity and, when the fracture remains reducible, may partially restore vertebral height.
6. Deflate and Remove the Balloon
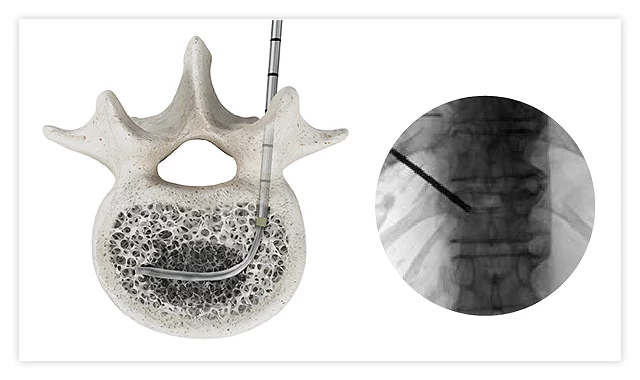
The balloon is deflated and removed. The sheath is repositioned to preserve access to the created cavity.
7. Place the Bone Cement
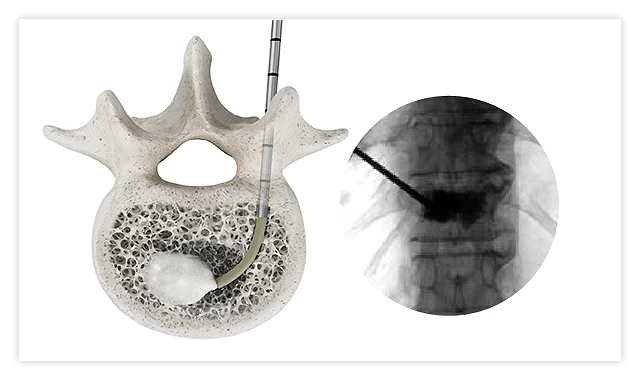
PMMA bone cement is delivered under continuous fluoroscopic observation. The goal is safe fracture stabilization with appropriate cement distribution, not maximum filling.
Procedure illustrations used with permission from Stryker. OmniCurve® is a registered trademark of Stryker. Illustrations are educational and do not represent every possible kyphoplasty technique.
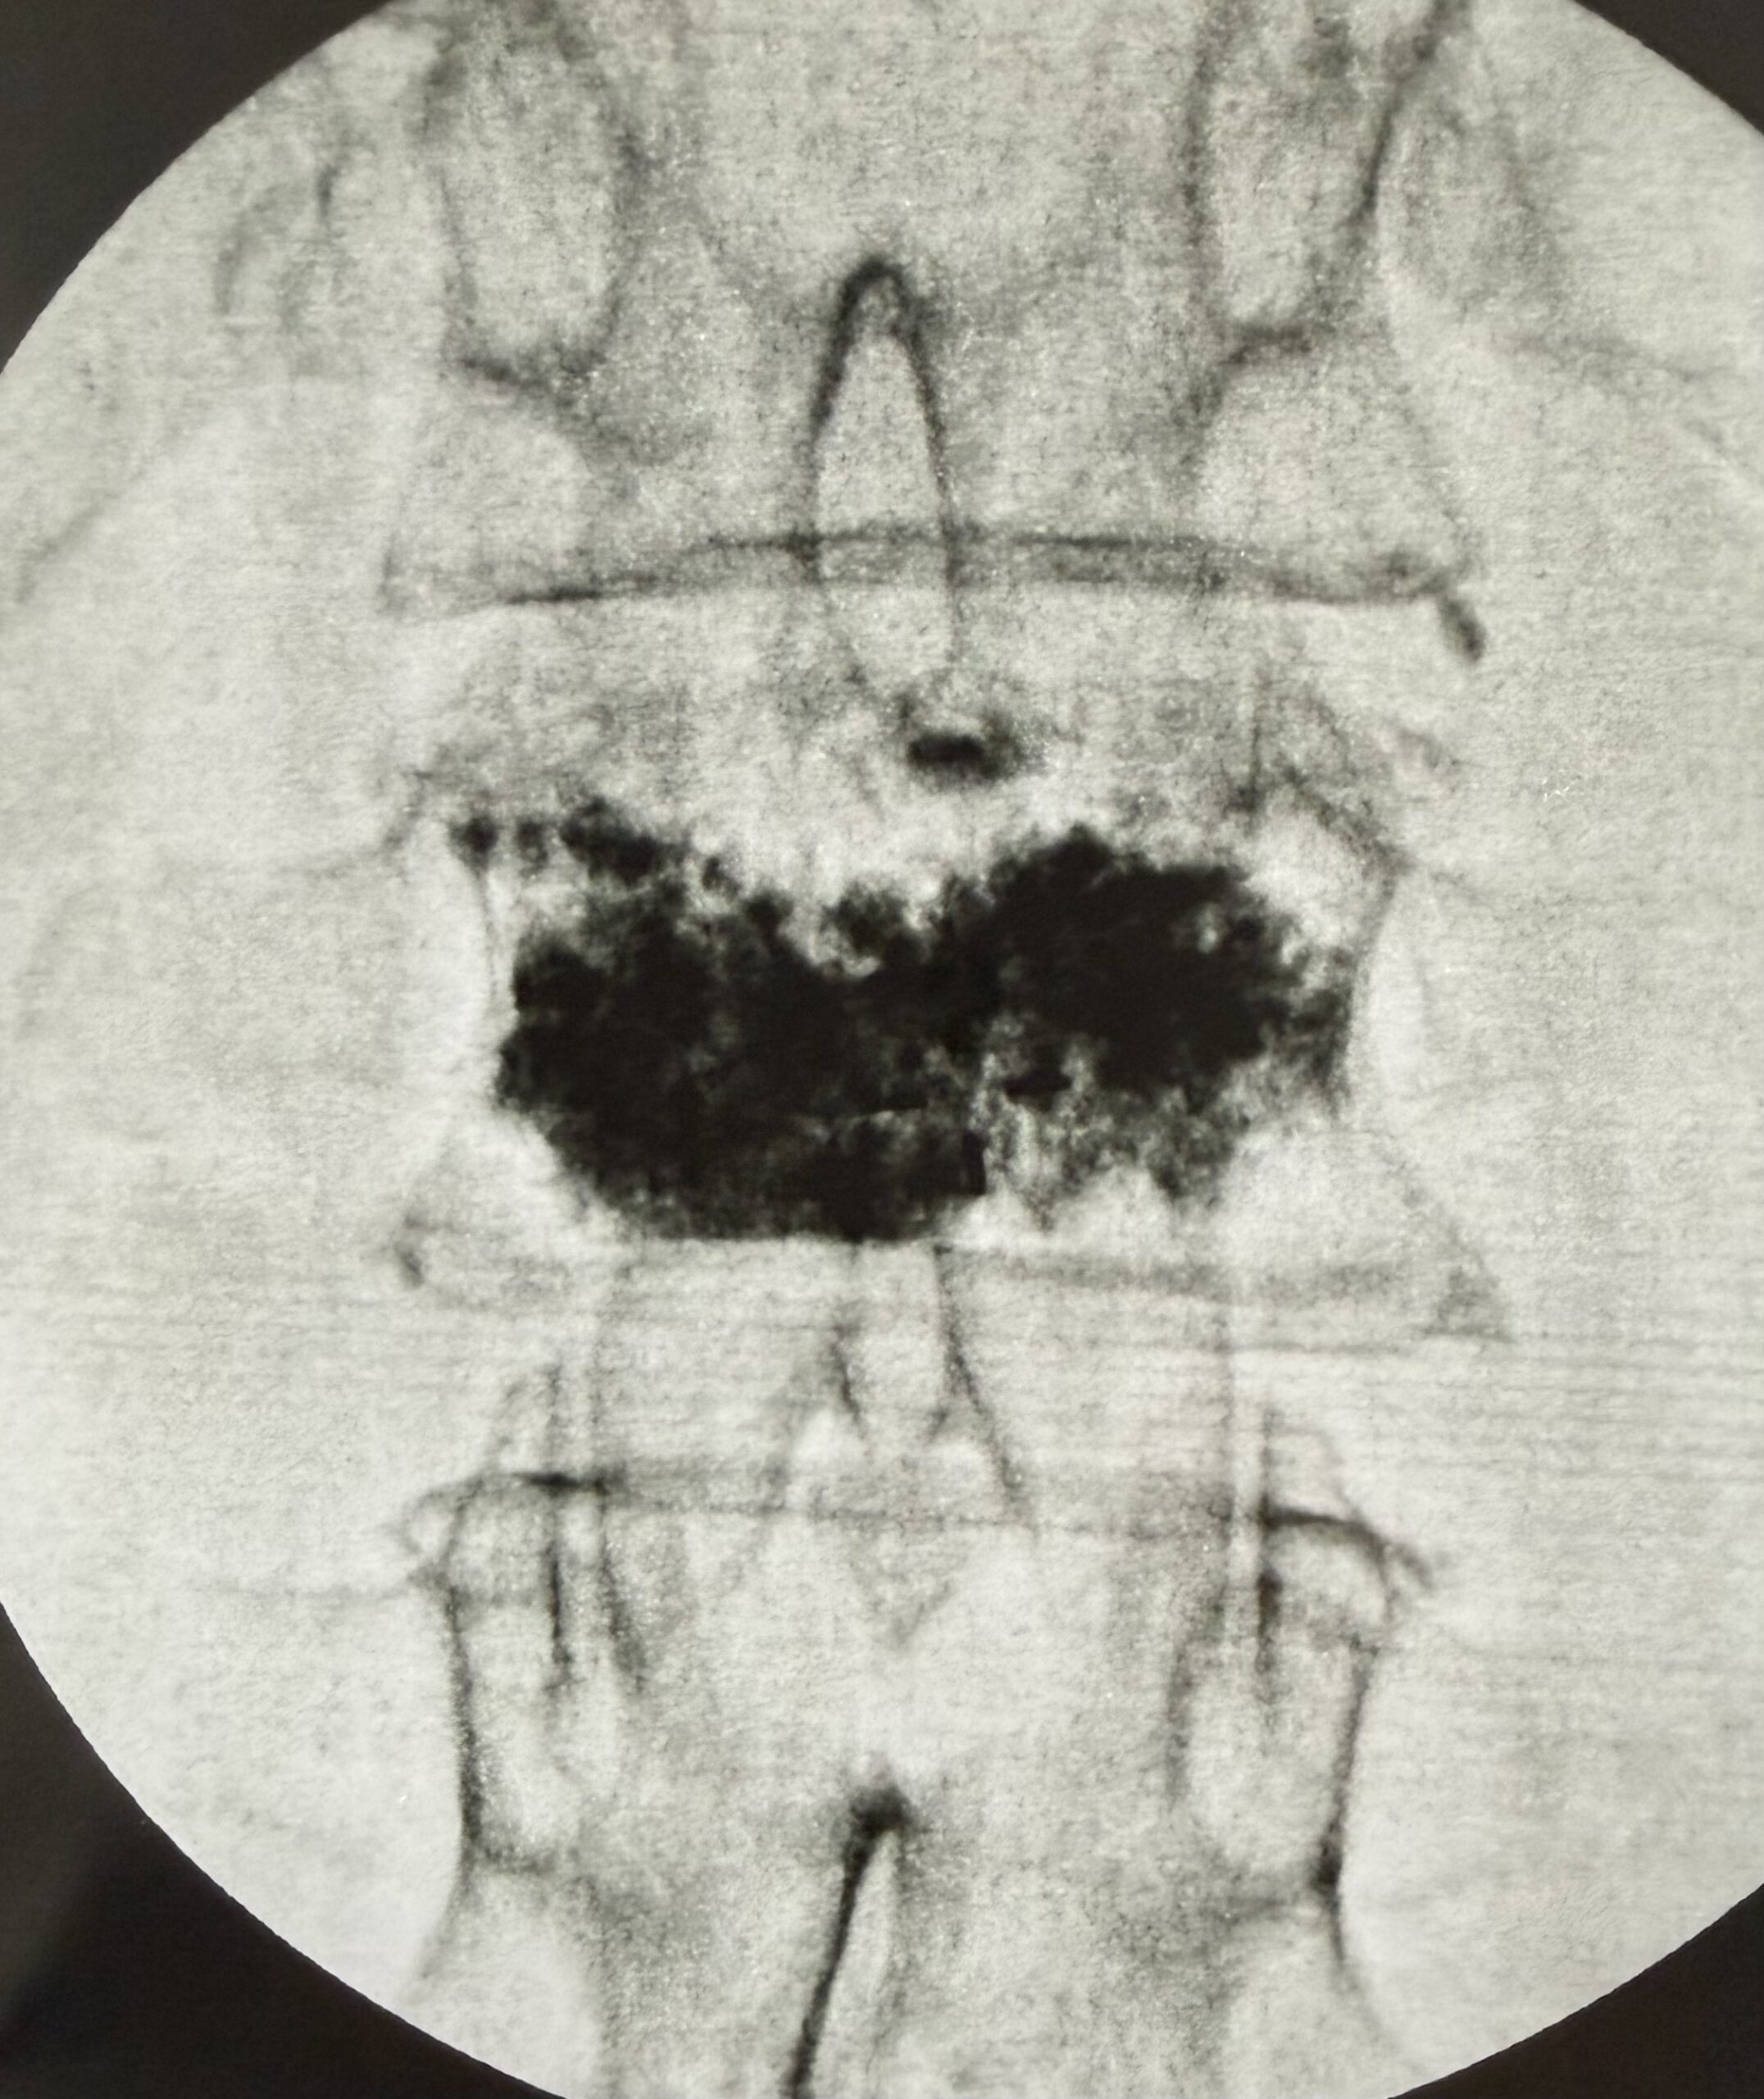
What Cement Placement Looks Like Under Fluoroscopy
AP and lateral fluoroscopic views help assess instrument position and cement distribution in real time. These are representative examples from Dr. Sharma’s clinical practice. Individual fracture anatomy, cement volume and cement distribution vary.

Recovery Monitoring
After the instruments are removed, the access site is covered with a small dressing. The patient is observed while the cement completes its initial hardening and the effects of sedation or anesthesia diminish. Walking often begins during recovery when medically safe, and same-day discharge is common after an uncomplicated procedure.
Kyphoplasty Versus Other Vertebral Augmentation Options
These procedures share a stabilization objective but use different access, cavity-creation and cement-delivery methods. No device is automatically best for every fracture.
| Approach | Practical Distinction | What Remains |
|---|---|---|
| Balloon kyphoplasty | A temporary balloon creates a cavity and may partially reduce a mobile fracture before cement placement | PMMA cement |
| Vertebroplasty | Cement is placed directly into the fracture without a balloon-cavity step | PMMA cement |
| SpineJack | Expandable titanium implants attempt controlled internal fracture reduction and remain in place during cement stabilization | Titanium implant plus PMMA cement |
| RF-TVA | Radiofrequency-activated cement preparation and targeted delivery are used to control the augmentation construct | PMMA cement |
Balloon kyphoplasty often shows less radiographic cement leakage than vertebroplasty in comparative studies, but most detected leaks are asymptomatic and serious leakage complications can occur with either procedure. It is too strong to claim that the balloon step makes kyphoplasty categorically safer.
Timing, Cement Amount and Rapid Pain Relief
These questions deserve concise answers on the parent page and deeper treatment in their dedicated child articles.
Does Timing Matter?
Timing is individualized. A recent meta-analysis associated kyphoplasty performed within four weeks with better average pain outcomes than later treatment, but the included studies were heterogeneous and did not establish a universal deadline. Immediate treatment is not necessary for every fracture, and prolonged mandatory waiting is not appropriate when pain is severe, mobility is deteriorating and imaging confirms an active treatable fracture.
Is More Cement Better?
No. The goal is not to fill the vertebra with the maximum possible volume. The goal is adequate stabilization with safe, controlled distribution through the clinically important fracture region. Vertebral size, cement viscosity, fracture morphology, cortical defects and distribution matter more than a universal volume target.
Why Can Pain Improve Quickly?
Some patients improve within the first day or two, while others recover gradually. The most accepted explanation is stabilization of painful fracture micromotion. Reduced mechanical irritation and changes in fracture-site signaling may also contribute. Thermal or basivertebral-nerve mechanisms remain plausible but incompletely established explanations rather than proven primary mechanisms.
Recovery After Kyphoplasty
Same-day discharge is common after uncomplicated treatment, but it is not guaranteed. Recovery depends on the fracture cause, number of levels, baseline mobility, anesthesia and overall medical condition.
- Walking commonly begins after observation and medical clearance.
- Access-site soreness may continue for several days.
- Fracture pain may improve rapidly or gradually over days to weeks.
- A responsible adult should drive the patient home after sedation or anesthesia.
- Driving should wait until sedating medication has been stopped and movement, attention and vehicle control are safe.
- Lifting, bending and exercise restrictions are individualized.
- Traumatic and cancer-related fractures may require additional restrictions or coordinated treatment.
- Rehabilitation may later address gait, posture, strength, balance and fall prevention.
Numbness and weakness are not typical fracture-pain symptoms to dismiss. New or worsening neurological findings require prompt reassessment.
What Does the Evidence Show?
Evidence quality and treatment context differ by fracture cause.
Osteoporotic Fractures
The FREE randomized trial found faster improvement in pain, function, mobility and quality of life with balloon kyphoplasty than nonsurgical care in selected patients with acute painful fractures. A 2025 systematic review and meta-analysis reported moderate-certainty evidence of better average pain relief from one through 12 months and early disability improvement, but disability differences were not significant at six or 12 months. It found no significant difference in new vertebral-fracture risk.
These are group-level results. They do not establish that every active fracture requires a procedure or that every patient will improve.
Traumatic Fractures
A 2024 systematic review reported encouraging clinical and radiographic results for kyphoplasty and expandable implants in selected traumatic thoracolumbar fractures. Most available evidence was nonrandomized, and augmentation was sometimes combined with posterior fixation. It therefore supports careful selection rather than routine cement augmentation for every traumatic fracture.
Cancer-Related Fractures
The CAFE randomized trial found improved function at one month with kyphoplasty compared with nonsurgical management in selected patients with cancer and painful vertebral compression fractures. The trial allowed control-group crossover after one month and was industry funded. Kyphoplasty should be viewed as one component of a multidisciplinary cancer-fracture plan.
Mobility and Survival
Vertebral compression fractures are associated with frailty, immobility and increased mortality in older adults. Observational database studies have reported survival associations favoring vertebral augmentation, but treatment selection, baseline health and mobility create important confounding. Kyphoplasty may help an appropriately selected patient regain mobility; it should not be marketed as a procedure proven to extend life or prevent death.
Risks and Limitations of Kyphoplasty
Kyphoplasty is minimally invasive, but it remains a spinal cement-augmentation procedure. Potential risks include:
- Cement leakage into veins, discs, soft tissues or the spinal canal
- Pulmonary cement embolism or another embolic complication
- Bleeding, hematoma or infection
- Nerve-root or spinal-cord injury
- Pedicle, cortical, vascular or other access-related injury
- Allergic reaction to cement, contrast or medication
- Anesthesia- or sedation-related complications
- Persistent pain or failure to improve
- A new or adjacent vertebral fracture
- Need for another augmentation procedure or a broader operation
Kyphoplasty also has important limitations. It does not treat osteoporosis or cancer, directly decompress the spinal canal, reliably correct an old fixed deformity, guarantee height restoration or prevent future fractures. It may not relieve pain arising from another structure.
What If Pain Continues or Gets Worse?
Mild access-site soreness can occur and should generally improve. Persistent, severe, escalating or newly different pain should be evaluated rather than automatically labeled normal recovery. Possible causes include residual fracture pain, a new vertebral fracture, facet or sacroiliac pain, infection, bleeding, neural compression or symptomatic cement leakage.
Cement seen outside the vertebral body on imaging is often asymptomatic. Its location and corresponding neurological or cardiopulmonary symptoms determine clinical importance.
Learn how postoperative pain is evaluated.
Read Pain After Kyphoplasty: What Is Normal, Possible Causes, Cement Leakage and Warning Signs for the full evaluation pathway.
Seek urgent evaluation for new or worsening weakness, loss of bowel or bladder control, saddle-region numbness, fever, wound drainage, chest pain, shortness of breath, fainting or rapidly escalating pain.
Does Kyphoplasty Treat Osteoporosis?
No. Kyphoplasty stabilizes the treated fracture but does not reverse the underlying loss of bone strength. A vertebral fragility fracture is an important warning that the patient remains at risk for another fracture.
A bone-health plan may include:
- DEXA testing when appropriate
- Vitamin D, calcium and secondary-cause laboratory evaluation
- Nutrition review
- Osteoporosis medication selected for the patient’s fracture risk and medical history
- Weight-bearing and resistance exercise when safe
- Balance training and fall-risk reduction
- Review of medications and conditions that increase fall or fracture risk
Alternatives and Additional Treatments
Depending on the fracture and the patient, options may include:
- Analgesic treatment, activity modification and gradual mobilization
- Bracing when appropriate
- Osteoporosis treatment and fall prevention
- Vertebroplasty
- SpineJack
- Radiofrequency-targeted vertebral augmentation
- Biopsy or tumor ablation with augmentation when clinically appropriate
- Radiation or systemic cancer therapy
- Surgical fixation, decompression or reconstruction for instability, deformity or neural compression
Related Kyphoplasty and Compression Fracture Resources
- Vertebral Compression Fracture
- Vertebral Augmentation
- Vertebroplasty
- SpineJack Versus Balloon Kyphoplasty
- Radiofrequency-Targeted Vertebral Augmentation
- Pain After Kyphoplasty
- How Much Cement Is Enough in Kyphoplasty?
- Why Kyphoplasty Can Relieve Pain Quickly
- Compression Fractures, Mobility and Life Expectancy
Does Your Compression Fracture Fit Kyphoplasty?
A focused evaluation can determine whether the fracture remains active and whether kyphoplasty, another augmentation approach, continued nonsurgical care or surgical evaluation is most appropriate.
Frequently Asked Questions
What is kyphoplasty?
Is kyphoplasty appropriate for osteoporotic, traumatic and cancer-related fractures?
Who may be a candidate for kyphoplasty?
Why is MRI often important before kyphoplasty?
How is kyphoplasty different from vertebroplasty?
How is kyphoplasty different from SpineJack?
Is more cement better during kyphoplasty?
Does timing matter for kyphoplasty?
How long is recovery after kyphoplasty?
What are the risks of kyphoplasty?
What if pain continues after kyphoplasty?
Does kyphoplasty treat osteoporosis or cancer?
References
- American College of Radiology. ACR Appropriateness Criteria: Management of Vertebral Compression Fractures, 2022 update. Read source →
- Wardlaw D, Cummings SR, Van Meirhaeghe J, et al. Efficacy and safety of balloon kyphoplasty compared with nonsurgical care for vertebral compression fracture: a randomized controlled trial. Lancet. 2009. Read source →
- Encalada S, et al. The effectiveness of balloon kyphoplasty compared with conservative treatment for osteoporotic vertebral compression fractures: a systematic review and meta-analysis. Interventional Pain Medicine. 2025. Read source →
- Moura DL, et al. The role of kyphoplasty and expandable intravertebral implants in the treatment of traumatic vertebral compression fractures: a systematic review. 2024. Read source →
- Berenson J, et al. Balloon kyphoplasty versus nonsurgical fracture management for painful vertebral body compression fractures in patients with cancer: the CAFE randomized trial. Lancet Oncology. 2011. Read source →
- Khan MA, et al. The effect of time to balloon kyphoplasty on osteoporotic vertebral compression fractures: a systematic review with meta-analysis. North American Spine Society Journal. 2024. Read source →
- Rose LD, Bateman G, Ahmed A. Clinical significance of cement leakage in kyphoplasty and vertebroplasty: a systematic review. European Spine Journal. 2024. Read source →
- Noriega D, et al. Randomized comparison of implantable titanium vertebral augmentation with balloon kyphoplasty in osteoporotic vertebral compression fractures: the SAKOS study. Spine Journal. 2019. Read source →
- Stryker. OmniCurve curved balloon system: procedure workflow and product information. Read source →