MILD Procedure
“I can walk farther when I lean over a shopping cart. Could the MILD procedure help me walk upright with less leg pain?”
That pattern may reflect neurogenic claudication from lumbar spinal stenosis. MILD is designed for a specific form of stenosis in which a thickened ligamentum flavum contributes importantly to narrowing of the spinal canal.
The MILD procedure, also called minimally invasive lumbar decompression or percutaneous image-guided lumbar decompression, removes small portions of lamina and excess ligamentum flavum through a small access portal under fluoroscopic guidance.
The purpose is to create more room for nerves in the lower spinal canal and improve walking-limited symptoms of neurogenic claudication. MILD does not place an implant, fuse the spine, remove an entire lamina or treat every cause of lumbar spinal stenosis.
Quick Answer
- MILD treats lumbar central-canal stenosis when hypertrophic ligamentum flavum is an important contributor.
- The procedure is usually performed with local anesthetic and monitored sedation rather than general anesthesia.
- Small portions of bone and thickened ligament are removed under fluoroscopic guidance.
- No permanent implant is left behind, and the procedure does not fuse the spine.
- Patients usually go home the same day. Activity progression depends on soreness, balance, sedation and individual instructions.
- MILD may not be sufficient when stenosis is mainly caused by extensive bone, a large disc herniation, instability or deformity.
Dr. Amit Sharma & our minimally invasive pain & spine team.
What Is the MILD Procedure?
The mild® procedure is an FDA-cleared, minimally invasive lumbar decompression technique. It is performed through a small portal using specialized instruments and indirect imaging rather than a large incision or direct endoscopic view.
The physician uses fluoroscopy and contrast imaging to identify the treatment area. A small amount of lamina is removed to create access, and the hypertrophic ligamentum flavum is partially debulked. The objective is to reduce posterior compression of the central canal while preserving most of the surrounding bone, muscle and ligament.
MILD is one procedure within a larger decompression category.
For a comparison with endoscopic decompression, interspinous devices and laminectomy, visit the Minimally Invasive Lumbar Decompression guide.
What Does MILD Treat?
MILD is primarily used for symptomatic lumbar spinal stenosis with neurogenic claudication when thickened ligamentum flavum contributes to narrowing of the central spinal canal.
Lumbar Spinal Stenosis
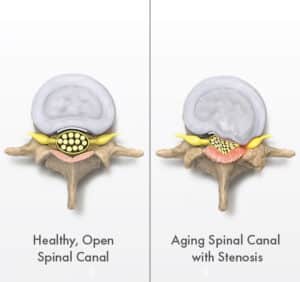
Lumbar spinal stenosis means that space for nerves in the lower spine has become narrowed. Common contributors include thickened ligamentum flavum, enlarged facet joints, bone spurs, disc bulging, spondylolisthesis and degenerative deformity.
MILD targets only the posterior ligament-and-lamina component that can be reached safely through its percutaneous approach. It does not remove all of the other possible contributors to stenosis.
Ligamentum Flavum Hypertrophy
The ligamentum flavum lines the back of the spinal canal. With age and degeneration, it can thicken or buckle inward when the spine extends. This can reduce the room available for nerves, especially when other degenerative changes are also present.
Clinical studies of MILD commonly required imaging evidence that hypertrophic ligamentum flavum contributed to central stenosis. A thickness of at least 2.5 millimeters was used in major trials, but a measurement alone does not establish candidacy. Symptoms, examination findings, the full MRI and other pain generators must also be evaluated.

What Symptoms May Fit MILD Candidacy?
The most characteristic symptom pattern is neurogenic claudication. Patients may report:
- Leg or buttock pain that develops with standing or walking
- Heaviness, aching, tingling or numbness in one or both legs
- Reduced standing time or walking distance
- Improvement after sitting, bending forward or leaning on a shopping cart
- Symptoms that return when the patient stands upright again
- Difficulty completing errands, exercise or daily activities because of limited walking tolerance
Some patients also have lower-back pain, but MILD is not intended simply for nonspecific axial back pain. The strongest clinical fit is walking- or standing-related leg and buttock symptoms that correspond with lumbar central stenosis.
Not every leg symptom is neurogenic claudication.
Peripheral artery disease, neuropathy, hip disease and nerve-root compression can produce overlapping symptoms. A careful evaluation is needed before attributing walking limitation to lumbar stenosis.
Who May Be a Candidate for the MILD Procedure?
A patient may be considered for MILD when the clinical picture and imaging identify lumbar central stenosis with an important ligamentum-flavum component.
Features That May Support Candidacy
- Neurogenic claudication that limits standing, walking or daily function
- Lumbar central-canal stenosis that matches the symptom level
- Hypertrophic ligamentum flavum contributing to the narrowing
- Persistent symptoms despite an appropriate trial of conservative care
- No more convincing vascular, hip, peripheral-nerve or other explanation
- No instability, deformity or neurological emergency requiring a different procedure
- A preference for an implant-free decompression when the anatomy is suitable
Conservative Treatment Usually Tried First
Before MILD, patients commonly try diagnosis-appropriate treatment such as activity modification, physical therapy, a home exercise program, medications and, in selected cases, an epidural steroid injection. The duration and documentation required vary according to the medical situation and insurance policy.
When MILD May Not Be the Right Procedure
MILD is a focused treatment. It may be insufficient or inappropriate when the dominant problem is:
- A large disc herniation requiring direct removal
- Severe bony lateral-recess or foraminal stenosis
- Marked spinal instability or higher-grade spondylolisthesis
- Significant scoliosis or deformity
- Fracture, tumor or active spinal infection
- Predominantly vascular claudication
- Hip arthritis, peripheral neuropathy or another nonspinal walking limitation
- Progressive weakness, cauda equina symptoms or another condition requiring urgent surgical evaluation
If hypertrophic bone is a major contributor, endoscopic lumbar decompression or surgical laminectomy may permit a broader direct decompression. If instability is clinically important, decompression may need to be combined with stabilization or fusion.
How Is the MILD Procedure Performed?
MILD is generally performed in an outpatient procedure setting using fluoroscopic guidance.
Fluoroscopy and contrast imaging help identify the stenotic level and monitor the epidural space.
After local anesthetic is administered, specialized instruments are introduced through a small posterior portal.
A limited amount of bone is removed to access and partially debulk the hypertrophic ligamentum flavum.
The instruments are removed, a small dressing is applied and the patient is monitored before same-day discharge.
Procedure time depends on the number of levels, anatomy and technical factors. Many cases are completed in less than an hour, but the full visit also includes preparation, sedation, monitoring and discharge.
Does MILD Require General Anesthesia?
MILD is commonly performed with local anesthetic and monitored sedation rather than general anesthesia. The exact plan depends on the facility, patient health, airway risk, anxiety, positioning tolerance and physician judgment.
Even without general anesthesia, patients may receive sedating medication and should follow the facility’s fasting and transportation instructions. A responsible adult driver is generally required when sedation is used.
For broader preparation guidance, including medications, blood thinners, diabetes treatment, fasting and driving, review Preparing for Spine Injection. Individual instructions from the procedural team always take priority.
Recovery After the MILD Procedure
Patients usually go home the same day after a period of observation. Mild soreness, bruising or stiffness at the access site may occur.
The First 24 to 48 Hours
- Follow the facility’s driving restriction after sedation.
- Keep the small dressing and access site clean according to instructions.
- Use prescribed or approved pain medication only as directed.
- Walk short, safe distances as tolerated unless instructed otherwise.
- Avoid strenuous lifting, repeated bending and high-impact activity until cleared.
Returning to Activity
Some patients resume light routine activity within a few days. Others need longer because of soreness, deconditioning, balance limitations or other health conditions. Return to work depends on job demands and recovery rather than a universal 24-hour rule.
Improvement may be gradual. The procedure creates more space for nerves, but it does not immediately reverse deconditioning or every source of pain. A walking program or physical therapy may be recommended as symptoms permit.
Call the treating team promptly for concerning symptoms.
Seek medical advice for fever, drainage, increasing redness, severe or rapidly worsening pain, new weakness, new bowel or bladder dysfunction or numbness in the saddle region. Emergency symptoms require urgent evaluation.
Potential Benefits of MILD
For appropriately selected patients, potential advantages include:
- Targeted treatment of hypertrophic ligamentum flavum
- A small percutaneous access portal rather than an open incision
- No permanent implant
- No spinal fusion
- Preservation of most surrounding bone, muscle and ligament
- Same-day discharge in most cases
- Use of local anesthetic and monitored sedation in many patients
- A steroid-free decompression option
- The possibility of improved standing and walking tolerance
These are potential advantages, not guaranteed outcomes. Benefit depends heavily on whether thickened ligament is a clinically important cause of the patient’s symptoms.
What Does the Evidence Show?
MILD has been evaluated in randomized trials, prospective studies and longer-term observational follow-up. The evidence is most applicable to patients with neurogenic claudication, central lumbar stenosis and hypertrophic ligamentum flavum.
MiDAS ENCORE
MiDAS ENCORE randomized 302 Medicare patients to MILD or epidural steroid injection. Published results reported greater improvement in disability and pain measures in the MILD group at one year, with follow-up of MILD participants through two years. The trial compared selected patients with neurogenic claudication and verified central stenosis related to ligamentum-flavum hypertrophy; its conclusions should not be generalized to every form of stenosis.
MOTION Trial
The MOTION randomized trial compared MILD plus conventional medical management with conventional medical management alone. Published follow-up has reported sustained improvement in patient-reported outcomes and walking tolerance in the MILD group. Five-year results were published in 2026, adding longer-term information about durability in the study population.
Cleveland Clinic Five-Year Cohort
In a retrospective Cleveland Clinic cohort of 75 patients, 9 patients underwent open decompression at the treated level during five-year follow-up. Stated another way, 88% did not undergo same-level open decompression during that period. Because this was an observational cohort without a randomized comparison group, the result does not prove that MILD prevented surgery in every patient.
Evidence quality and applicability matter.
Several important MILD studies were sponsored by the device manufacturer or included investigators with disclosed industry relationships. This does not invalidate the findings, but it should be considered alongside study design, selection criteria and independent clinical judgment.
What MILD Does Not Do
MILD is not a universal substitute for lumbar decompression surgery. It does not:
- Remove an entire lamina
- Directly visualize the nerves through an endoscope
- Remove a large disc herniation
- Fully remove severe bony lateral-recess or foraminal stenosis
- Correct scoliosis or spinal deformity
- Stabilize an unstable spinal segment
- Fuse the spine
- Guarantee avoidance of future surgery
- Treat every cause of lower-back or leg pain
Partial improvement may occur when several pain generators coexist. For example, MILD may address the ligamentous component of central stenosis while facet pain, foraminal narrowing, neuropathy or hip disease continues to cause symptoms.
MILD Procedure Risks and Safety Considerations
MILD has demonstrated a favorable safety profile in published studies, but it remains an invasive spinal procedure. Possible risks include:
- Temporary soreness, bruising or increased pain
- Bleeding or hematoma
- Infection
- Allergic or kidney-related reaction to contrast, when relevant
- Dural puncture or cerebrospinal-fluid leak
- Nerve irritation or nerve injury
- Radiation exposure from fluoroscopy
- Sedation-related complications
- Incomplete decompression or limited symptom relief
- Need for another procedure or later surgery
Risk varies with anatomy, anticoagulant use, infection status, medical conditions, number of levels and procedural technique. Patients should not stop blood thinners independently; medication changes must be coordinated with the prescribing and procedural clinicians.
MILD vs Epidural Injection, Endoscopic Decompression and Laminectomy
| Treatment | What It Does | Best Clinical Fit | Important Limitation |
|---|---|---|---|
| Epidural steroid injection | Places anti-inflammatory medication around irritated spinal nerves | Selected radicular or stenosis-related inflammation | Does not remove ligament or bone |
| MILD | Removes small portions of lamina and hypertrophic ligamentum flavum | Central stenosis with neurogenic claudication and a major ligamentous component | Limited ability to address extensive bone, disc or instability |
| Endoscopic decompression | Directly visualizes and removes selected bone and ligament | Central or lateral-recess stenosis with a larger bony component | More extensive procedure and recovery than MILD |
| Laminectomy | Performs a broader direct surgical decompression | Severe, multilevel or anatomically complex stenosis | Greater procedural burden; fusion may be considered if instability exists |
The right choice depends on the anatomy causing compression, symptom severity, neurological findings, medical risk and treatment goals. A smaller procedure is helpful only if it adequately treats the clinically important narrowing.
Does Medicare or Insurance Cover MILD?
Coverage depends on the patient’s plan, medical-necessity criteria, documentation, coding requirements and treatment setting. CMS maintains a national coverage framework for percutaneous image-guided lumbar decompression under Coverage with Evidence Development. Commercial-insurance and Medicare Advantage requirements vary.
Insurance coverage should be verified before treatment. Coverage is not the same as clinical candidacy, and an authorization does not guarantee payment if plan requirements are not met.
A Practical MILD Decision Pathway
MILD Patient Brochures
Frequently Asked Questions About the MILD Procedure
What is the MILD procedure?
MILD is a percutaneous, image-guided lumbar decompression procedure that removes small portions of lamina and hypertrophic ligamentum flavum to create more room in the central spinal canal. It leaves no permanent implant and does not fuse the spine.
Who is a candidate for MILD?
Candidates commonly have neurogenic claudication, lumbar central stenosis and imaging evidence that thickened ligamentum flavum contributes to the narrowing. Symptoms, examination, imaging and prior treatment response must be considered together.
Does MILD require general anesthesia?
MILD is commonly performed with local anesthetic and monitored sedation rather than general anesthesia. The exact anesthesia plan depends on the patient, procedure setting and treating team.
How long does the MILD procedure take?
Many MILD procedures are completed in less than an hour, although time varies with anatomy and the number of treated levels. Preparation, monitoring and discharge make the total visit longer.
What is recovery like after MILD?
Patients usually go home the same day. Mild soreness may occur, and many resume light activity within a few days. Driving, lifting, work and exercise instructions should be individualized.
Does MILD place an implant or fuse the spine?
No. MILD removes small amounts of tissue through a percutaneous portal. It does not leave a permanent implant and does not perform a spinal fusion.
Is MILD the same as a laminectomy?
No. MILD removes limited portions of lamina and ligament under indirect imaging. A laminectomy permits a broader direct surgical decompression and may be more appropriate for severe, extensive or complex stenosis.
Can MILD prevent future back surgery?
Some patients may avoid or delay a larger operation after successful MILD treatment, but this cannot be guaranteed. Disease progression, incomplete decompression or another spinal problem may eventually require additional treatment.
Does Medicare cover the MILD procedure?
Coverage depends on the applicable Medicare framework, plan requirements, diagnosis, documentation and treatment setting. The office should verify benefits and authorization requirements before treatment.
References
- Benyamin RM, Staats PS, MiDAS ENCORE Investigators. MILD is an effective treatment for lumbar spinal stenosis with neurogenic claudication: MiDAS ENCORE randomized controlled trial. Pain Physician. 2016. Read source →
- Staats PS, et al. Long-term safety and efficacy of minimally invasive lumbar decompression: two-year results of MiDAS ENCORE. Regional Anesthesia and Pain Medicine. 2018. Read source →
- Deer TR, et al. The MOTION Study: a randomized controlled trial with objective real-world outcomes for lumbar spinal stenosis treated with the MILD procedure. Pain Medicine. 2022. Read source →
- Deer TR, et al. The MOTION Study: two-year results of a real-world randomized controlled trial of the MILD procedure. 2024. Read source →
- Costandi SJ, et al. Three-year results of the MOTION randomized controlled trial for lumbar spinal stenosis using the MILD procedure. 2025. Read source →
- Deer TR, et al. Five-year results of the MOTION randomized controlled trial for lumbar spinal stenosis using the MILD procedure. 2026. Read source →
- Mekhail N, et al. The durability of minimally invasive lumbar decompression in patients with symptomatic lumbar spinal stenosis: long-term follow-up. Pain Practice. 2021. Read source →
- Centers for Medicare & Medicaid Services. Percutaneous Image-guided Lumbar Decompression for Lumbar Spinal Stenosis. Updated January 23, 2026. Read source →
- American Academy of Orthopaedic Surgeons. Lumbar Spinal Stenosis. Read source →
About Dr. Amit Sharma
Amit Sharma, MD is an interventional spine and pain-management physician who evaluates lumbar spinal stenosis and performs image-guided and minimally invasive spine procedures on Long Island.
Medical Disclaimer
This article is intended for general educational purposes and does not replace an individualized medical evaluation, diagnosis or treatment recommendation. MILD is not appropriate for every patient with lumbar spinal stenosis. Candidacy, preparation, anesthesia, risks, expected recovery and insurance coverage vary according to symptoms, anatomy, medical history, procedural setting and applicable policy. Seek urgent medical care for new weakness, loss of bowel or bladder control, saddle-region numbness or rapidly progressive neurological symptoms.
Last medically reviewed: September 2026