SpineJack Procedure vs Balloon Kyphoplasty | Amit Sharma, MD
“Is SpineJack simply kyphoplasty with a metal implant, and is one procedure better than the other?”
Both procedures stabilize selected vertebral compression fractures with bone cement, but they reduce the fracture differently. SpineJack leaves an expandable titanium implant inside the vertebra; balloon kyphoplasty removes the balloon before cement is placed. The best fit depends on the fracture, anatomy and treatment objective.
SpineJack is an implant-assisted vertebral augmentation procedure for selected painful vertebral compression fractures. A collapsed titanium implant is positioned inside the fractured vertebral body and expanded in an attempt to reduce part of the collapse. Polymethylmethacrylate, or PMMA, bone cement is then placed around the implant to stabilize the reconstruction.
The procedure should not be described as universally better than balloon kyphoplasty. Comparative studies have reported radiographic advantages in selected patients, but both approaches can improve pain and function, and the evidence does not establish that SpineJack is superior for every fracture.
Quick Answer
- SpineJack: An expandable titanium implant remains inside the vertebra and is surrounded by PMMA cement.
- Balloon kyphoplasty: A temporary balloon creates a cavity and may partially reduce the fracture; the balloon is removed before PMMA cement is placed.
- Both: Are minimally invasive cement-augmentation procedures intended to stabilize an appropriately selected painful fracture.
- Selection: Depends on fracture activity, reducibility, collapse pattern, posterior-wall integrity, pedicle anatomy, neurological status and the patient’s overall condition.
What Is the SpineJack Procedure?
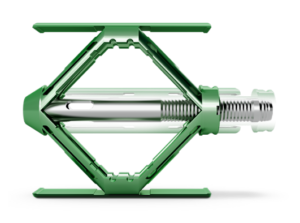
SpineJack is a percutaneously implanted fracture-reduction system. The implant is made of titanium alloy and is introduced through a small working channel in a collapsed configuration. Once positioned within the vertebral body, it is expanded vertically to help elevate the compressed endplate when the fracture remains reducible. PMMA bone cement is injected around the expanded implant to stabilize the treated vertebra.
The US Food and Drug Administration cleared SpineJack for reduction of painful vertebral compression fractures and for use with specified PMMA bone cement. Current US labeling includes selected fractures caused by osteoporosis, selected traumatic Type A fractures under the AO/Magerl classification, and compression fractures associated with malignant lesions such as multiple myeloma or osteolytic metastasis. FDA clearance does not mean every fracture within those categories is an appropriate candidate.
The titanium implant does not replace PMMA cement. The implant supplies an internal expansion mechanism, while the cement stabilizes the reduction and fractured vertebral body.
Which Compression Fractures Can SpineJack Treat?
Cause is only one part of the decision. The fracture must also be painful, clinically relevant and suitable for implant placement and cement augmentation.
Osteoporotic Compression Fractures
This is the most established clinical application. A patient may be considered when an acute or subacute fracture causes focal pain and loss of mobility, remains active on MRI or other appropriate imaging, and has not improved adequately with an individualized period of conservative treatment.
Selected Traumatic Compression Fractures
Current US labeling includes selected traumatic Type A vertebral compression fractures, with or without posterior instrumental fixation. This does not include every traumatic or burst fracture. Type B or C injuries, major ligament disruption, translation, important canal compromise or neurological loss require broader spine-trauma evaluation and may need fixation or decompression rather than augmentation alone.
Fractures Associated With Malignant Lesions
Current labeling also includes compression fractures associated with myeloma or osteolytic metastatic disease. Vertebral augmentation may stabilize a painful fracture, but it does not treat the underlying cancer. Candidacy requires coordination with oncology and review for epidural tumor, spinal-cord compression, vertebral destruction, mechanical instability and the possible roles of biopsy, radiation, tumor ablation or surgical fixation.
How the SpineJack Procedure Works
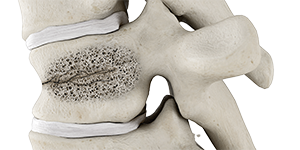
Symptoms, examination and MRI or other imaging are reviewed to determine whether the fracture is active and responsible for the pain.
The patient is positioned and receives local anesthesia with monitored sedation or general anesthesia, depending on the fracture, medical condition and procedure plan.
Working cannulas are advanced through the pedicles under fluoroscopic guidance. Implant number and access are selected for the individual anatomy.
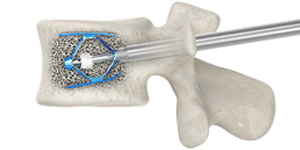
The collapsed titanium implant is positioned within the vertebral body and expanded in a controlled direction in an attempt to reduce part of the fracture.
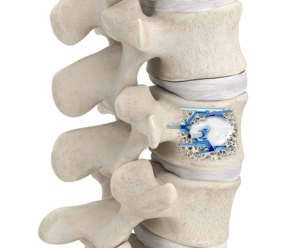
PMMA cement is delivered around the expanded implant under imaging guidance to stabilize the treated vertebra.
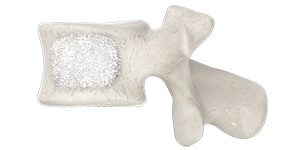
After the instruments are removed, the patient is monitored. Same-day discharge is common after an uncomplicated procedure, although observation needs vary.
SpineJack Versus Balloon Kyphoplasty
Both are vertebral augmentation procedures. The practical difference is what reduces the fracture and what remains after reduction.
| Feature | SpineJack | Balloon Kyphoplasty |
|---|---|---|
| Reduction method | Expandable titanium implant | Temporary inflatable balloon |
| What remains | Titanium implant plus PMMA cement | PMMA cement; the balloon is removed |
| Mechanical concept | The expanded implant remains in place while cement stabilizes the reconstruction | The balloon creates a cavity and may reduce part of the collapse before removal and cement placement |
| Bone cement | Required | Required |
| Height restoration | Directed expansion may restore and maintain height in selected reducible fractures | Restoration varies with fracture mobility, balloon position and anatomy |
| Evidence base | Smaller, device-specific literature including randomized comparisons | Broader vertebral-augmentation literature across fracture types |
| Clinical outcome | Can improve pain and function in appropriately selected patients | Can improve pain and function in appropriately selected patients |
Neither procedure is automatically superior. SpineJack may be considered when controlled internal expansion and maintenance of reduction are important and the fracture anatomy can safely accommodate the implant. Balloon kyphoplasty may be preferred when the fracture, pedicle anatomy, treatment goal or operator plan favors a temporary balloon and cement-only construct.
Who May Be a Candidate for SpineJack?
The MRI does not make the decision by itself. Symptoms, examination, fracture age, activity on imaging, mechanical stability and procedural anatomy must identify the same clinically important problem.
| Findings Supporting Consideration | Findings Requiring Another Pathway or More Evaluation |
|---|---|
| Acute or subacute focal pain corresponding with a compression fracture | Old, healed or non-mobile collapse without evidence that the fracture remains active |
| MRI edema or another accepted sign of an active fracture | Pain more consistent with a disc, facet joint, muscle, another vertebra or systemic condition |
| Persistent pain or mobility loss despite appropriate nonsurgical care | Progressive weakness, spinal-cord compression or another neurological emergency |
| A fracture that remains mechanically reducible | Important retropulsion, severe canal compromise or unstable Type B or C traumatic injury |
| Pedicles and vertebral anatomy that can accommodate the access route and implant | Fracture geometry or anatomy that prevents safe implant placement |
| Acceptable anesthesia, infection and coagulation risk | Active infection, uncorrected bleeding risk or severe uncontrolled medical disease |
When Urgent Surgical Evaluation Is More Appropriate
Vertebral augmentation does not directly decompress the spinal canal or replace instrumented stabilization. New or progressive weakness, loss of bowel or bladder control, saddle-region numbness, substantial canal compromise, spinal-cord compression or a mechanically unstable fracture requires urgent evaluation for a broader surgical pathway.
Potential Benefits of SpineJack
For an appropriately selected fracture, potential benefits include:
- Internal mechanical reduction of a mobile vertebral compression fracture
- Stabilization of painful fracture movement with PMMA cement
- Attempted restoration of vertebral height and local alignment
- A retained implant designed to support the expanded position
- Small percutaneous access routes rather than an open reconstruction
- Same-day discharge after many uncomplicated procedures
These are treatment objectives, not guaranteed outcomes. Height restoration depends on fracture age, mobility and morphology. Pain may persist when the treated fracture is not the only pain generator or when neurological compression, deformity or another disease remains untreated.
Recovery After the SpineJack Procedure
SpineJack is commonly performed as an outpatient procedure. Some patients experience early improvement in fracture pain, while others improve gradually. Recovery depends on the fracture cause, number of treated levels, anesthesia, baseline mobility and overall health.
- Walking commonly begins after observation and medical clearance.
- Access-site soreness may continue for several days.
- A responsible adult should drive the patient home after sedation or anesthesia.
- Driving should wait until sedating medication has been stopped and movement, attention and vehicle control are safe.
- Lifting, bending and exercise restrictions are individualized.
- Bone-health evaluation remains important because augmentation treats the fracture, not the underlying osteoporosis.
- Cancer-related and traumatic fractures may require additional treatment and different activity restrictions.
New pain after initial improvement should be evaluated. It may reflect a new compression fracture, incomplete relief from the treated level or another spinal or nonspinal pain source. The Pain After Kyphoplasty guide explains why pain can continue after vertebral augmentation and when repeat imaging may be considered.
Evidence and Limitations
The SAKOS randomized trial compared an implantable titanium vertebral augmentation system with balloon kyphoplasty in selected patients with recent painful osteoporotic compression fractures. SpineJack was noninferior for the trial’s primary composite clinical outcome. The study also reported greater midline vertebral-height restoration and fewer adjacent fractures in the SpineJack group during the study period.
Those findings require context. The trial involved a selected osteoporotic-fracture population, approximately one year of follow-up and manufacturer support. Differences in radiographic measurements do not automatically produce superior pain, function or quality of life for every patient. The adjacent-fracture finding should not be converted into a promise that SpineJack prevents future fractures.
A smaller randomized pilot trial and its three-year follow-up reported improvement with both SpineJack and balloon kyphoplasty, with some radiographic advantages for SpineJack. The sample was small. A later systematic review and meta-analysis found broadly similar pain improvement among vertebroplasty, balloon kyphoplasty and vertebral body implants, while implant-based augmentation showed radiographic advantages. Differences among studies, devices, fracture types and follow-up limit firm comparisons.
Clearance establishes that the device may be marketed for its labeled use. It does not establish that SpineJack is better than balloon kyphoplasty, vertebroplasty or another approach for every patient.
Risks and Safety Considerations
SpineJack is minimally invasive, but it remains an implant and cement-augmentation procedure. Potential risks include:
- Cement leakage into veins, discs, soft tissues or the spinal canal
- Pulmonary cement embolism or another embolic complication
- Bleeding, hematoma or infection
- Nerve-root or spinal-cord injury
- Pedicle, cortical, vascular or other access-related injury
- Implant malposition, asymmetric expansion or inadequate fracture reduction
- Failure of the implant to expand or release as intended
- Allergic reaction to implant, cement, contrast or medication
- Anesthesia- or sedation-related complications
- Persistent or worsening pain
- A new or adjacent vertebral fracture
- Need for another augmentation procedure or a broader operation
Severe escalating pain, new weakness, new bowel or bladder dysfunction, saddle-region numbness, fever, drainage, chest pain or shortness of breath requires prompt medical evaluation. Chest pain, difficulty breathing or new severe neurological symptoms may require emergency care.
Alternatives to SpineJack
The appropriate alternative depends on fracture activity, stability, cause and neurological status. Options may include:
- Analgesic treatment, bracing and gradual mobilization
- Osteoporosis evaluation, medication and fall-risk reduction
- Balloon kyphoplasty
- Vertebroplasty
- Radiofrequency-targeted vertebral augmentation
- Biopsy, tumor ablation, radiation or systemic cancer treatment when malignancy is involved
- Instrumented fixation, decompression or reconstruction when instability, deformity or neural compression requires a broader operation
Related Compression Fracture Resources
- Kyphoplasty
- Vertebral Compression Fracture
- Vertebroplasty
- Radiofrequency-Targeted Vertebral Augmentation
- Pain After Kyphoplasty
Which Vertebral Augmentation Approach Fits Your Fracture?
A focused evaluation can determine whether the fracture remains active and whether SpineJack, balloon kyphoplasty, vertebroplasty, another augmentation approach or surgical evaluation is most appropriate.
Frequently Asked Questions
What is the SpineJack procedure?
How is SpineJack different from balloon kyphoplasty?
Does SpineJack use bone cement?
Does the SpineJack implant remain permanently?
Is SpineJack better than balloon kyphoplasty?
Can SpineJack restore vertebral height?
Does SpineJack prevent adjacent compression fractures?
Which fracture types are included in current US SpineJack labeling?
How long is recovery after SpineJack?
What if pain continues after SpineJack?
References
- US Food and Drug Administration. SpineJack System 510(k) Summary, K223294. Expanded US indications include selected osteoporotic, traumatic Type A and malignant-lesion vertebral compression fractures. Read source →
- Noriega D, et al. A prospective, international, randomized, noninferiority study comparing an implantable titanium vertebral augmentation device with balloon kyphoplasty in osteoporotic vertebral compression fractures: the SAKOS study. Spine Journal. 2019. Read source →
- Noriega DC, et al. Safety and clinical performance of kyphoplasty and SpineJack procedures in the treatment of osteoporotic vertebral compression fractures: a pilot, monocentric, randomized study. Osteoporosis International. 2016. Read source →
- Noriega D, et al. Long-term safety and clinical performance of kyphoplasty and SpineJack procedures in the treatment of osteoporotic vertebral compression fractures: a three-year follow-up study. 2019. Read source →
- Marcia S, et al. Clinical and radiologic outcomes of vertebral augmentation using expandable implants versus vertebroplasty or balloon kyphoplasty: systematic review and meta-analysis. American Journal of Neuroradiology. 2023. Read source →
- American College of Radiology. ACR Appropriateness Criteria: Management of Vertebral Compression Fractures. 2022 update. Read source →